Health
BBT Slow to Rise After Ovulation: Causes, Charts & What to Do




Anyone searching for kossma.com about us is likely trying to answer a few practical questions: Who owns Kossma Beauty? Where are its products made? What makes its formulas different from conventional skincare, and what should shoppers know before buying?
Kossma Beauty is an Arizona-based skincare brand founded by herbalist and licensed aesthetician Stephanie Peña. The company centers its identity on small-batch, animal-fat-based skincare, regenerative and organic botanicals, and formulas designed without essential oils or high-PUFA seed oils.
Rather than following the familiar plant-oil-heavy model used by many natural beauty brands, Kossma has built its product philosophy around ingredients such as grass-fed tallow, ghee, jojoba, herbal extracts, plant resins, beeswax, hydrosols, and selected lower-PUFA oils. That distinctive formulation approach is the main reason the brand has developed a recognizable position in the natural and tallow skincare market.
Kossma Beauty at a Glance
| Detail | Kossma Beauty |
|---|---|
| Founder | Stephanie Peña |
| Launched | 2019 |
| Main focus | Tallow-based and botanical skincare |
| Production | Handcrafted in an Arizona apothecary |
| Formulation approach | Animal fats, whole herbs and PUFA-aware oils |
| Essential oils | Brand says its core formulas avoid them |
| Product categories | Cleansers, hydrosols, balms, oils, serums, body care and supplements |
| Ingredient sourcing | U.S. regenerative farms, organic farms and selected international partners |
| Customer guarantee | 30-day guarantee, subject to return-policy restrictions |
Kossma states that its formulas are produced in its Arizona apothecary and that much of its sourcing emphasizes regenerative U.S. farms, organic ingredients, direct-trade partners and ECOCERT-certified materials.
Who Founded Kossma Beauty?
Kossma Beauty was founded by Stephanie Peña, whose interest in herbal medicine developed during her aesthetics training in 2003. According to the company’s founder story, she had been creating animal-fat-based skincare for years before turning those formulations into a commercial brand.
Peña says her interest in whole-body wellness, herbalism and traditional fats became more significant while exploring nutrition and holistic health for her family. She began developing skincare products using animal fats and botanical ingredients and later sold formulations at local markets.
That work eventually became Kossma Beauty, which officially launched in 2019. The company’s current positioning still reflects Peña’s combination of aesthetics, herbal preparation and interest in traditional wellness practices.
Why Was Kossma Created?
Kossma was developed around a disagreement with common formulation practices in both mainstream and natural skincare.
The brand argues that many products rely too heavily on essential oils, synthetic fragrance and oils rich in polyunsaturated fatty acids. Kossma therefore developed what it calls a “PUFA-aware” approach that favors animal fats and carefully selected oils alongside whole botanical extracts.
It is important to distinguish the company’s formulation philosophy from universally accepted dermatological guidance. Claims that particular categories of seed oils are inherently inflammatory or harmful to skin are broader than the evidence established for every ingredient, concentration and formulation.
For shoppers, the useful takeaway is simpler: Kossma has a clearly defined ingredient philosophy. People specifically looking for skincare without essential oils and with a strong emphasis on tallow and traditional fats can quickly determine whether that philosophy matches their preferences.
What Does “PUFA-Aware Skincare” Mean at Kossma?
PUFA stands for polyunsaturated fatty acid. Kossma uses the term “PUFA-aware” to describe its preference for oils and fats that fit the company’s approach to oxidation, fatty-acid balance and skin-barrier support.
Instead of eliminating every plant-derived oil, Kossma selectively uses ingredients such as jojoba, meadowfoam, squalane and other oils it considers compatible with its formulation philosophy. Its Reishi Rose Tallow Beauty Oil, for example, combines tallow with jojoba, meadowfoam seed oil, emu oil, botanical extracts and other ingredients.
This distinction matters because “PUFA-aware” should not be interpreted as “seed-oil-free” across every formula. Consumers who need to avoid a specific ingredient should always check the complete ingredient list of the individual product rather than relying only on category-level marketing.
The Role of Tallow in Kossma Products
Tallow is one of Kossma Beauty’s signature ingredients.
Rendered animal fat has been used historically in soaps, balms and personal-care preparations. Kossma uses grass-fed tallow in multiple moisturizing products and combines it with herbs, resins, waxes and plant-derived oils.
The best-known example is the Tallow Beauty Balm, which contains grass-fed tallow alongside jojoba oil, tucuma butter, frankincense resin, calendula, chamomile, rose, cocoa butter and beeswax cappings. The company positions it primarily as a rich moisturizer for dry, sensitive and mature skin.
Tallow-based skincare will not appeal to everyone. Vegans and consumers who prefer exclusively plant-derived cosmetics will naturally want to consider alternatives, while people specifically interested in animal-fat skincare may see Kossma’s specialization as a defining feature.
How Kossma Uses Herbs and Botanical Extracts
Kossma is not simply a tallow brand. Herbal preparations form another major part of its identity.
The company maintains an ingredient library covering materials such as calendula, chamomile, aloe vera, frankincense, marshmallow root, reishi mushroom and numerous other botanicals. Kossma says herbs may come from regenerative or organic U.S. farms as well as selected direct-trade international suppliers.
Many formulas rely on infusions or extracts rather than essential oils. This allows the brand to incorporate aromatic and medicinal plants while maintaining its stated essential-oil-free approach.
Frankincense Without Relying on Essential Oil
Frankincense appears frequently across Kossma’s product range, but the brand often uses resin, hydrosol or specialized extracts instead of frankincense essential oil.
Its New Moon Intensive Age Serum, for example, lists squalane, frankincense resin, boswellic extract, pearl powder and cacao extract.
The distinction is useful for customers who enjoy botanical skincare but intentionally avoid concentrated essential oils because of personal preference or skin sensitivity.
Are Kossma Products Completely “Natural”?
“Natural” is not always a useful binary description in modern cosmetic formulation.
Although Kossma emphasizes traditional fats, herbs and naturally derived materials, some products contain functional cosmetic ingredients and preservatives. The brand openly explains, for example, that it uses gluconolactone and sodium benzoate as a preservation system in appropriate water-based formulas.
This is an important positive sign from a formulation-transparency perspective. Water-containing products generally require an effective preservation strategy to reduce microbial contamination.
Consumers should therefore judge products by their complete ingredient lists and formulation purpose rather than assuming that “natural” automatically means preservative-free.
Where Does Kossma Source Its Ingredients?
Ingredient sourcing is a major part of the Kossma brand story.
The company says its grass-fed tallow comes from a regenerative U.S. farm, while herbs are sourced from American organic or regenerative farms and family-owned fair-trade cooperatives. Some products also use ingredients certified under ECOCERT standards.
Kossma also states that some herbs are grown specifically for its products and that additional botanicals are obtained through direct international trade relationships.
These sourcing details help explain why Kossma positions itself closer to an apothecary-style producer than a conventional mass-market beauty company.
What Products Does Kossma Beauty Sell?
Kossma has grown beyond a single tallow balm. Its current catalog includes multiple skincare formats and wellness-related products.
Major categories include:
- Tallow balms and moisturizing oils
- Facial cleansers
- Hydrosols and facial mists
- Serums
- Exfoliating products
- Body-care products
- Skincare kits and bundles
- Shampoo products
- Pro-metabolic supplements
The company’s collection page currently separates products into categories such as cleansers and hydrosols, moisturizers and serums, skincare, best sellers and supplements.
Tallow Beauty Balm
The Tallow Beauty Balm is one of Kossma’s flagship products. It combines grass-fed tallow with jojoba, herbal extracts, cocoa butter and beeswax and is designed primarily as a moisturizing finishing balm.
Reishi Rose Tallow Beauty Oil
The Reishi Rose formula is a lighter facial oil built around jojoba, tallow, emu oil, botanical butter and extracts including reishi, rose and frankincense. Kossma recommends applying it while the skin remains damp after using a hydrosol.
Chamomile Cleansing Gel
Not everything in the catalog is tallow based. Kossma’s Chamomile Cleansing Gel uses aloe vera, coconut- and sugar-derived surfactants, glycerin, chamomile extract, panthenol, allantoin and preservatives.
This broader range makes the company more accurately described as an animal-fat and herbal skincare brand rather than simply a tallow balm seller.
Who Is Kossma Beauty Best Suited For?
Kossma may be particularly relevant to consumers who prefer:
- Tallow or other animal-fat-based skincare
- Essential-oil-free formulas
- Shorter or recognizable ingredient lists
- Small-batch skincare
- Botanical extracts and traditional herbal ingredients
- Products emphasizing U.S. regenerative sourcing
- Rich moisturizers for dry or mature-feeling skin
The brand also publishes routines for normal, dry, sensitive and breakout-prone skin, although product recommendations should still be adjusted to individual tolerances and dermatological needs.
People with allergies, acne, eczema or highly reactive skin should avoid assuming that a “natural,” “ancestral” or tallow-based formula will automatically be suitable for them.
What to Check Before Buying from Kossma
A strong brand story should never replace basic product research.
Before ordering, consider these practical checks:
- Read the full ingredient list. Individual Kossma products can contain dairy-derived ingredients, beeswax, honey, animal fats or botanicals that may not suit every customer.
- Match texture to your skin. Rich balms can behave very differently from hydrosols, cleansers and lightweight oils.
- Patch-test unfamiliar products. Botanical ingredients can still trigger individual sensitivities.
- Separate cosmetic claims from medical treatment. Skincare can support moisture, texture and appearance, but persistent acne, dermatitis or other skin conditions may require professional medical care.
- Check the current return policy. Guarantees often include exclusions or procedural requirements.
These steps are more useful than buying solely because a product is described as clean, natural or ancestral.
Reviews and Customer Feedback
Kossma displays substantial customer feedback directly across its product pages. Its website currently highlights thousands of five-star reviews across the catalog, while individual products such as the Tallow Beauty Balm, Chamomile Cleansing Gel and Reishi Rose Beauty Oil show hundreds of customer ratings.
Reviews can be useful for understanding texture, scent, packaging and how products fit into real routines. However, testimonials remain individual experiences and should not be treated as proof that a skincare product will produce the same result for every person.
For best results, use reviews alongside ingredient lists, formulation details and your own skin history.
Kossma Customer Service and 30-Day Guarantee
Kossma provides customer support for orders, shipping, returns, wholesale inquiries, product questions, press and affiliate requests.
According to its contact page, customer service operates Monday through Friday from 9 a.m. to 3 p.m. MST, with responses generally expected within two business days.
The company also advertises a 30-day guarantee. Customers who are dissatisfied can contact support regarding a refund, although Kossma notes that return-policy restrictions apply.
Checking those restrictions before purchasing is especially worthwhile for bundles, sale items or products subject to hygiene-related return conditions.
What Makes the Kossma Brand Different?
Kossma’s clearest differentiator is not simply that it sells tallow.
Its brand identity combines several elements that are less commonly found together:
- Animal-fat-centered skincare
- Essential-oil avoidance
- A PUFA-aware formulation philosophy
- Herbal infusions and traditional resins
- Regenerative ingredient sourcing
- Small-batch apothecary production
- A broader interest in nutrition and traditional wellness
Kossma says it was already developing this approach when the company launched in 2019 and describes itself as an early pioneer of PUFA-aware, animal-forward skincare.
Whether a consumer agrees with every aspect of that philosophy is a separate question. From a branding perspective, however, the company has developed a much more specific formulation identity than simply calling itself “clean beauty.”
Frequently Asked Questions About Kossma.com
Who owns Kossma Beauty?
Kossma Beauty was founded by Stephanie Peña, an herbalist and licensed aesthetician whose work with animal-fat skincare and herbal preparations predates the company’s 2019 launch.
Where is Kossma Beauty located?
Kossma says its formulas are handcrafted in its Arizona apothecary.
When was Kossma founded?
Kossma Beauty launched in 2019, according to the company’s founder and affiliate pages.
Is Kossma a tallow skincare brand?
Yes. Tallow is central to many of its best-known products, although the company also sells cleansers, hydrosols, serums and other formulas that are not primarily tallow based.
Does Kossma use essential oils?
Kossma positions its skincare around formulas made without essential oils. Instead, products may use whole herbs, resins, hydrosols and botanical extracts.
Is Kossma vegan?
Many Kossma products are not vegan because the brand deliberately uses animal-derived ingredients such as tallow, ghee, beeswax, goat’s milk, emu oil and other traditional ingredients depending on the formula.
Does Kossma offer returns?
Kossma advertises a 30-day guarantee, subject to its return-policy restrictions. Customers can contact the company’s support team for assistance.
Conclusion: Understanding the kossma.com about us Story
The kossma.com about us story centers on founder Stephanie Peña’s interest in herbalism, animal fats and traditional wellness practices. Since launching in 2019, Kossma Beauty has built its identity around handcrafted Arizona production, tallow-based moisturizers, whole botanical extracts, regenerative sourcing and its distinctive PUFA-aware formulation philosophy.
For consumers, the most useful way to evaluate Kossma is to look beyond broad labels such as “natural” or “ancestral.” Review the exact ingredients, understand the role of animal-derived materials, consider your own skin needs and distinguish the company’s formulation philosophy from medical claims.
That combination of transparency and careful product-by-product evaluation gives shoppers a much clearer picture of what Kossma Beauty represents—and whether its approach belongs in their skincare routine.

If you are searching for hmrprogram.com about us, you are probably trying to understand who is behind HMR, how the weight-management program works, and whether its approach has a credible history.
HMR, originally known as Health Management Resources, is a U.S.-based weight-management program founded in 1983. Its approach combines structured eating, portion-controlled foods, behavioral change strategies, physical activity, and optional coaching rather than relying on calorie counting alone.
This guide looks beyond a basic company description. It explains HMR’s history, program structure, research background, digital tools, and the practical considerations people should understand before choosing a weight-loss program.
HMR Program Quick Facts
| Detail | Information |
|---|---|
| Brand | HMR Program |
| Original name | Health Management Resources |
| Founded | 1983 |
| Founder | Dr. Lawrence Stifler |
| Core focus | Weight loss and long-term lifestyle change |
| Main approach | Structured meals, fruits and vegetables, behavioral strategies, activity, and coaching |
| Primary programs | Phase 1 Structured Plan and Phase 2 Flex Plan |
| Coaching | Available with qualifying subscription plans |
| Digital support | HMR mobile app powered by Solyce Health |
| Website | hmrprogram.com |
| Current website operator | HMR Program, Inc. |
HMR’s current terms identify HMR Program, Inc. as the company operating the website and HMR mobile application. The site is intended for adults aged 18 or older who reside in the United States or its territories or possessions.
What Is HMR Program?
HMR is a structured weight-management system designed to make food decisions simpler while helping participants develop behaviors that may support longer-term weight control.
Instead of requiring users to calculate every calorie, carbohydrate, or point, HMR’s structured plans rely heavily on pre-portioned HMR shakes, entrées, and other foods. Depending on the plan, participants add fruits, vegetables, and other approved foods.
The company describes four major elements behind its approach: structured nutrition, lifestyle change, support, and long-term weight management.
That distinction matters. HMR is not simply an online store selling meal replacements; its broader program is built around using food structure as a tool while encouraging changes in eating patterns and physical activity.
The History Behind HMR
How Health Management Resources Started
HMR was founded in 1983 by behavioral psychologist Dr. Lawrence Stifler. According to HMR’s published history, Stifler worked with people experiencing overweight and obesity and focused on changing repeatable behaviors rather than concentrating only on why an individual had gained weight.
The early concept was deliberately simple: make appropriate food choices easier while concentrating attention on behaviors that could have a meaningful effect on weight management.
Dr. Stifler’s biographical information also confirms that he founded Health Management Resources in 1983 after academic work that included teaching at Boston University and Harvard.
From Clinical Programs to HMR at Home
HMR initially operated largely through hospitals and healthcare settings. The company says its program was offered exclusively through hospitals before becoming available directly to consumers through its HMR at Home model.
This clinical background helps explain why HMR remains more structured than many conventional diet plans.
Today’s consumer program allows people to order HMR foods, follow structured or flexible plans at home, receive coaching in eligible plans, use online educational resources, and track behaviors through a companion app.
How the HMR Weight-Loss Approach Works
HMR currently separates its consumer offering into two main stages or approaches.
Phase 1: The Structured Diet Plan
Phase 1 is intended for people who want a highly structured approach. HMR’s current standard plan describes a daily framework of three HMR shakes, two HMR entrées, and five cups of fruits and vegetables.
The purpose of this structure is to reduce uncertainty around meal decisions. Participants know in advance which categories of food form the core of the plan instead of creating every meal from scratch.
HMR markets Phase 1 particularly toward people who have more weight to lose or who prefer stronger food structure.
Phase 2: A More Flexible Approach
Phase 2 introduces considerably more flexibility.
Rather than depending primarily on HMR products throughout the day, participants can use selected HMR foods to replace higher-calorie meals or snacks while incorporating a broader range of conventional foods. HMR currently recommends approximately two HMR foods per day as one way of using the flexible plan.
Phase 2 can therefore serve two different purposes: continued gradual weight loss or support after an initial period of more structured dieting.
Why Behavioral Change Is Central to HMR
One of the most important things to understand from the hmrprogram.com about us story is that HMR’s philosophy has always extended beyond packaged food.
Its program materials emphasize changing repeated behaviors related to eating and activity. HMR’s historical approach includes increasing fruit and vegetable consumption, increasing physical activity, using portion-controlled foods strategically, and learning how to handle situations that commonly make weight management difficult.
This is relevant because losing weight and maintaining weight are not identical tasks.
A highly structured eating plan can reduce decisions during active weight loss. Long-term maintenance, however, requires someone to navigate restaurants, travel, holidays, social situations, grocery shopping, and ordinary meals without depending entirely on packaged foods.
HMR’s Phase 2 model is intended to help bridge that gap.
HMR Coaching and Member Support
HMR offers coaching alongside eligible subscription plans. Its support resources include Phase 1 and Phase 2 coaching sessions as well as recipes, educational articles, community resources, and guidance for new members.
The company currently reports that participants using its at-home program with coaching average greater weight loss over 12 weeks than people following its self-directed option. That figure comes from HMR’s own program data and should therefore be understood as a company-reported outcome rather than a guarantee of individual results.
Individual results can differ substantially based on starting weight, adherence, medical history, medications, activity, diet, duration of participation, and other factors.
Does HMR Have Research Behind It?
HMR has been studied in clinical and real-world settings, although readers should pay attention to the type of evidence being discussed.
A retrospective study published in PLOS ONE evaluated 500 participants in clinic-based HMR high-intensity lifestyle programs. Participants in that analysis experienced substantial average weight loss, although the research was observational rather than a randomized trial and involved clinic-based care that may differ from today’s standard home program.
Earlier research has also examined intensive HMR programs among people with severe obesity, including long-term follow-up after significant weight loss.
A broader review of commercial weight-loss programs found relatively large short-term losses in studies involving HMR, while also noting limitations in the available long-term evidence for very-low-calorie commercial approaches.
The practical takeaway is that evidence exists for HMR-style structured interventions, but results from intensive clinic programs should not automatically be assumed to apply identically to every current consumer plan.
The HMR App and Digital Tracking
HMR now includes a mobile companion app powered by Solyce Health.
The app is designed around tracking behaviors and progress. According to HMR, members can use it to access their tracker, weight log, program content, and parts of their HMR account experience.
Tracking is consistent with HMR’s broader behavior-change philosophy because it makes daily actions visible rather than focusing exclusively on scale weight.
For someone comparing digital weight-management programs, this is an important feature to consider. The experience is not limited to receiving food shipments; HMR increasingly combines physical products with coaching, education, tracking, and online support.
HMR and Weight-Loss Medication
HMR has also expanded its website to address prescription weight-loss medications.
The company does not state that it prescribes or dispenses these drugs itself. Instead, HMR says it connects potentially eligible individuals with independent licensed providers through a partnership with JRNYS, with prescribing decisions made by those providers.
HMR positions medication as one possible tool that can be combined with nutrition and behavioral support rather than as a replacement for lifestyle management.
Anyone considering prescription weight-loss treatment should discuss the potential benefits, contraindications, adverse effects, medication interactions, and appropriate monitoring with a qualified healthcare professional.
What Makes the HMR Model Different?
HMR sits somewhere between an ordinary self-directed diet and a traditional medically managed weight-loss clinic.
Its distinctive feature is the amount of structure built into the eating plan. Instead of asking participants to immediately master meal planning, portion estimation, shopping, calorie tracking, and restaurant decisions at the same time, the structured phase simplifies many of those choices.
The potential trade-off is that this approach depends considerably on HMR-branded foods during parts of the program. Anyone evaluating it should therefore consider not only potential weight-loss results but also cost, food preferences, convenience, sustainability, and how comfortably they can transition toward ordinary meals.
Important Questions to Ask Before Joining
Before choosing HMR—or any structured commercial weight-management program—consider these questions:
- Does the program fit your medical history and current medications?
- Are you comfortable regularly using meal replacements and prepared entrées?
- What will the complete monthly cost be once food, subscriptions, and optional services are included?
- Do you prefer independent dieting or regular coaching and accountability?
- How will you transition from structured meals to everyday food?
- Is the plan realistic during travel, work, family meals, and social events?
- What support is available if your weight plateaus or begins to increase again?
- Do you have a healthcare condition that requires individualized nutrition or medical supervision?
These questions can reveal whether a program fits your actual lifestyle instead of simply looking attractive during the first few weeks.
Safety and Medical Considerations
Structured low-calorie and very-low-calorie diets are not appropriate for everyone.
HMR’s own Terms of Sale state that some HMR products may be used as part of low-calorie or very-low-calorie diets and that such diets can require medical supervision. HMR also states that it does not provide medical advice and advises consumers to consult a physician before starting a diet program.
Its website terms similarly advise users to consult a physician before beginning a diet or exercise program because health risks depend on an individual’s medical condition.
This is especially important for people who have chronic medical conditions, take medications affected by changes in food intake or body weight, are considering a very-low-calorie diet, or have other circumstances requiring individualized care.
What to Look for When Evaluating HMR Success Stories
HMR publishes testimonials from participants who report substantial weight losses. The company also provides average-result disclosures alongside those testimonials, which is more informative than viewing the headline weight-loss figure alone.
A 50-, 75-, or 100-pound success story tells you what happened to one individual. It does not tell you the typical result for every participant.
When evaluating any weight-loss company, pay more attention to typical outcomes, study design, completion rates, length of follow-up, program intensity, and whether results came from a medically supervised clinic or a self-directed home program.
That is a more reliable approach than choosing a program based on the most dramatic transformation shown on a sales page.
Is HMR Simply a Meal-Replacement Company?
No. Meal replacements are a major component of HMR, but they are only one part of its stated model.
The broader system combines structured eating with behavior modification, physical activity, coaching, tracking, education, and a transition toward more flexible weight management. HMR also allows customers to purchase and use certain foods without joining a complete subscription plan.
That flexibility means two people can interact with HMR very differently: one might simply use shakes as convenient meals, while another may participate in the complete structured program with coaching.
Who May Find HMR’s Approach Appealing?
HMR may be most relevant to people who value clear rules and predictable meal choices rather than designing an entire diet themselves.
Someone who frequently struggles with portion decisions or deciding what to eat may appreciate the structured format. In contrast, a person who strongly prefers cooking from whole foods and having extensive menu freedom may find a meal-replacement-heavy phase less appealing.
Neither preference determines whether someone will succeed. The important issue is whether the program is realistic enough to follow consistently and whether an appropriate long-term eating strategy follows the structured phase.
hmrprogram.com about us: The Bigger Picture
The hmrprogram.com about us story begins with Health Management Resources, founded by behavioral psychologist Dr. Lawrence Stifler in 1983, but the modern HMR Program has developed into a broader combination of structured nutrition, behavioral support, coaching, digital tracking, and flexible weight-management options.
Its long history and published research distinguish HMR from many newly launched diet brands, but history alone does not determine whether the program is appropriate for a particular individual. The most useful way to evaluate HMR is to compare its level of structure, costs, food format, coaching, research, medical considerations, and long-term maintenance strategy against your own needs.
For anyone considering HMR for significant weight loss—particularly a low-calorie or medically intensive approach—the safest next step is to review the current program details and discuss the plan with a qualified healthcare professional who understands your health history.
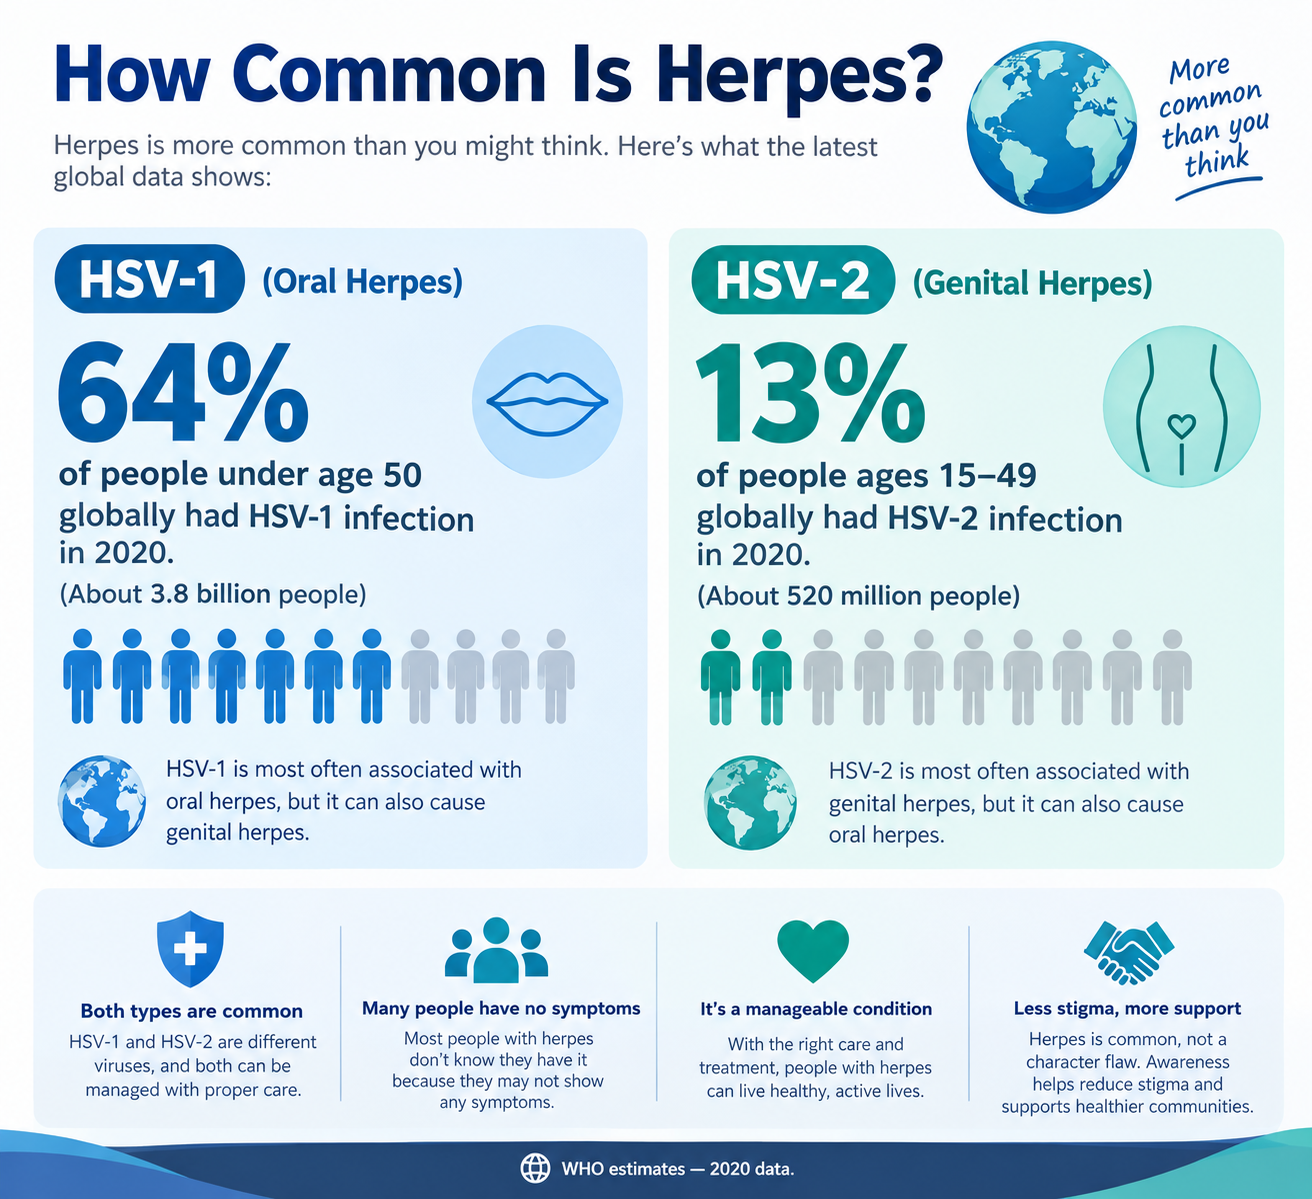
If you are wondering how many percentage of people have herpes, the answer depends on the type of herpes and the population being measured. Herpes simplex virus is extremely common worldwide, and many people who carry it never develop noticeable symptoms.
According to the World Health Organization (WHO), an estimated 64% of people under age 50 worldwide have HSV-1, while approximately 13% of people aged 15–49 have HSV-2. When both HSV-1 and HSV-2 infections affecting the genital area are considered, more than 1 in 5 people aged 15–49 worldwide are estimated to have genital herpes.
Herpes Statistics at a Glance
| Herpes measure | Estimated prevalence | Approximate number of people |
|---|---|---|
| HSV-1 worldwide, under age 50 | 64% | 3.8 billion |
| HSV-2 worldwide, ages 15–49 | 13% | 520 million |
| Genital herpes from HSV-1 or HSV-2, ages 15–49 | More than 20% | 846 million |
| Genital HSV-1, ages 15–49 | About 10% | 376 million |
| Symptomatic genital herpes during 2020, ages 15–49 | 5.3% | 205 million |
| U.S. HSV-1, ages 14–49, 2015–2016 | 47.8% | — |
| U.S. HSV-2, ages 14–49, 2015–2016 | 11.9% | — |
The global estimates above are based on WHO’s 2020 prevalence estimates, which remain the organization’s latest widely cited global estimates. The U.S. figures come from CDC/NHANES testing conducted in 2015–2016.
What Percentage of People Have Herpes Worldwide?
The broadest answer is that herpes affects billions of people.
WHO estimates that approximately 3.8 billion people younger than 50 had HSV-1 in 2020, equal to around 64% of that global age group. HSV-1 is most commonly associated with oral herpes, including cold sores, although it can also cause genital infections.
For HSV-2, WHO estimates approximately 520 million people aged 15–49 were infected in 2020, representing about 13% of the population in that age group. HSV-2 is primarily sexually transmitted and is the major cause of recurrent genital herpes.
Is It True That Most People Have Herpes?
That statement needs context.
If “herpes” refers to HSV-1, then yes—globally, a majority of people younger than 50 are estimated to carry the virus. A 64% prevalence means roughly two out of every three people in that age range have HSV-1.
That does not mean two-thirds of people have genital herpes. Many HSV-1 infections are oral infections acquired during childhood, often through nonsexual contact with saliva.
What Percentage of People Have Genital Herpes?
Genital herpes can be caused by either HSV-2 or genital HSV-1, so counting only HSV-2 understates the total number of people living with genital herpes.
WHO reported in December 2024 that approximately 846 million people aged 15–49 were living with genital herpes in 2020. That represents more than one in five people in this age group worldwide.
The estimate includes:
- About 520 million people with genital HSV-2
- About 376 million people with genital HSV-1
- Roughly 50 million people estimated to have both, preventing the two figures from simply being added together
This distinction explains why you may see different percentages when researching how common herpes is.
HSV-1 vs. HSV-2: Why the Percentages Are Different
HSV-1 and HSV-2 belong to the same herpes simplex virus family, but their typical transmission patterns differ.
HSV-1
HSV-1 most commonly causes oral herpes, including cold sores around the lips and mouth. Many infections are acquired in childhood through oral contact and never produce recognizable symptoms.
HSV-1 can also infect the genital area, particularly through oral-genital contact.
HSV-2
HSV-2 primarily affects the genital area and is generally transmitted through sexual contact.
Unlike genital HSV-1, HSV-2 is more likely to produce recurring genital outbreaks. WHO also notes an association between HSV-2 infection and an increased risk of acquiring HIV.
How Many People Have HSV-1?
WHO’s latest global estimate places HSV-1 prevalence at approximately 64% among people younger than 50.
That corresponds to around 3.8 billion people worldwide.
Most HSV-1 infections involve the mouth or surrounding area. However, WHO estimates approximately 376 million people aged 15–49 had genital HSV-1 infection in 2020.
These numbers demonstrate why saying simply that someone “has herpes” does not identify where the infection is located.
How Many People Have HSV-2?
An estimated 520 million people between ages 15 and 49 have HSV-2 worldwide, representing approximately 13% of people in that age group.
Put another way, that is approximately one in eight people aged 15–49 globally.
WHO reports that HSV-2 affects women more frequently than men, partly because sexual transmission is biologically more efficient from men to women. Prevalence also generally increases with age because HSV infection remains in the body for life.
What Percentage of Americans Have Herpes?
U.S. estimates differ from global figures, and the year of the dataset matters.
CDC’s nationally representative NHANES data for 2015–2016 found that among Americans aged 14–49:
- 47.8% tested positive for HSV-1
- 11.9% tested positive for HSV-2
HSV-1 prevalence ranged from 27.0% among people aged 14–19 to 59.7% among those aged 40–49. HSV-2 prevalence similarly increased with age.
The CDC has since collected HSV laboratory data for the 2021–2023 NHANES cycle, but that dataset was released in 2026 with restricted Research Data Center access rather than as the same type of publicly summarized national prevalence report. Therefore, the 2015–2016 figures should be clearly dated rather than presented as measurements from 2026.
Why Do Herpes Statistics Seem So Different?
A search for herpes prevalence can produce numbers ranging from around 10% to more than 60%. These figures are not necessarily contradictory.
They usually measure different things.
Different Virus Types
A statistic of around 64% commonly refers to HSV-1, while a rate near 13% usually refers specifically to HSV-2.
Oral vs. Genital Infection
HSV-1 can cause either oral or genital infection.
Someone who tests positive for HSV-1 antibodies may have an oral infection acquired in childhood, not genital herpes.
Different Age Groups
WHO’s HSV-1 figure covers people under age 50, while its HSV-2 estimate applies to people aged 15–49.
Comparing percentages without checking the age range can therefore be misleading.
Different Countries and Populations
Herpes prevalence varies geographically and among demographic populations.
Rates can also vary because studies use different testing methods, sampling techniques, dates, and definitions.
How Many People With Herpes Actually Have Symptoms?
Far fewer people experience noticeable herpes symptoms than carry the virus.
WHO estimates that about 205 million people aged 15–49, or 5.3%, experienced at least one symptomatic genital herpes episode during 2020.
Compare that with approximately 846 million people estimated to be living with genital herpes overall. The gap helps explain one of the most important facts about herpes: many infections are asymptomatic or unrecognized.
A person can therefore have HSV without ever seeing obvious sores.
Can You Have Herpes Without Knowing It?
Yes.
WHO states that most herpes simplex infections are asymptomatic or unrecognized. When symptoms do occur, they may include painful blisters or ulcers that can return periodically.
Mild symptoms may also be mistaken for other skin conditions, irritation, ingrown hairs, or pimples.
This means diagnosed cases alone cannot accurately show how common herpes is. Population prevalence studies often rely on antibody testing rather than counting only people who seek medical treatment.
Does a Cold Sore Mean You Have Herpes?
Cold sores are most commonly caused by HSV-1.
Because HSV-1 is a herpes simplex virus, someone with an HSV-1 cold sore does technically have a herpes infection. However, everyday use of the word “herpes” often refers specifically to genital herpes, which creates unnecessary confusion.
Oral HSV-1 is extremely common and often acquired long before a person becomes sexually active.
Can HSV-1 Cause Genital Herpes?
Yes.
HSV-1 can spread to the genital area through oral-genital contact. WHO estimates 376 million people aged 15–49 had genital HSV-1 in 2020.
This is why the statement “HSV-1 means oral herpes and HSV-2 means genital herpes” is an oversimplification.
Either virus can infect either location, although HSV-1 remains more strongly associated with oral infection and HSV-2 with genital infection.
Is Herpes Curable?
There is currently no treatment that eliminates HSV from the body.
Antiviral medicines can reduce symptoms, shorten outbreaks, and in some situations reduce the likelihood of transmission. WHO describes herpes as a lifelong infection whose symptoms can be treated even though the infection itself cannot currently be cured.
Commonly used antiviral medicines include acyclovir, valacyclovir, and famciclovir. Treatment decisions should be made with a qualified healthcare professional.
How Is Herpes Transmitted?
HSV spreads primarily through direct contact with infected skin, sores, saliva, or genital secretions.
Transmission can occur even when visible sores are absent because the virus may sometimes be present on the skin without obvious symptoms.
Risk-reduction strategies include:
- Avoiding oral or sexual contact during active outbreaks
- Using condoms consistently and correctly
- Discussing HSV status with sexual partners
- Following prescribed suppressive antiviral treatment when appropriate
- Avoiding sharing objects that have recently contacted saliva during an active oral outbreak
Condoms reduce transmission risk but cannot provide complete protection because HSV may be present on skin that a condom does not cover.
Should Everyone Be Tested for Herpes?
Testing decisions depend on symptoms, exposure history, pregnancy, sexual health concerns, and the type of test available.
A healthcare professional may test a fresh sore directly or use blood testing for HSV antibodies in certain circumstances. Blood tests have limitations, including their inability to reliably show the exact location of an HSV-1 infection.
People with genital sores, unusual lesions, a partner diagnosed with genital herpes, or concerns about recent exposure should discuss appropriate testing with a healthcare provider rather than relying on symptoms alone.
Pregnant people should inform their healthcare professional about known or suspected genital herpes because infection around the time of delivery can, in rare cases, be transmitted to a newborn.
Common Misunderstandings About Herpes Prevalence
“Only sexually active people get herpes”
Not necessarily. Oral HSV-1 is frequently acquired during childhood through nonsexual contact.
“Everyone with herpes gets outbreaks”
False. Many people never develop recognizable symptoms.
“HSV-1 is always oral”
False. HSV-1 can cause genital herpes.
“HSV-2 is the only genital herpes virus”
False. Both HSV-1 and HSV-2 can cause genital infections.
“A positive HSV-1 blood test proves genital herpes”
Not necessarily. HSV-1 antibodies show previous infection but generally cannot determine whether the infection is oral or genital.
What Do the Herpes Percentages Really Tell Us?
The most useful lesson from prevalence statistics is that HSV infection is common rather than exceptional.
Globally, around 64% of people under 50 have HSV-1, while 13% of people aged 15–49 have HSV-2. When genital infections caused by either virus are considered together, approximately 846 million people aged 15–49—more than one in five—are estimated to have genital herpes.
The figures also show why prevalence should not be confused with symptomatic disease. Only a fraction of infected people experience recognized outbreaks in any given year.
Frequently Asked Questions
What percentage of the world has herpes?
About 64% of people younger than 50 worldwide have HSV-1, according to WHO’s 2020 estimates. Approximately 13% of people aged 15–49 have HSV-2.
What percentage of people have genital herpes?
WHO estimates more than one in five people aged 15–49 worldwide have genital herpes caused by HSV-1, HSV-2, or both. That represents approximately 846 million people.
Is herpes present in 80% of the population?
Not according to the current WHO global estimate for HSV-1 in people under 50, which is approximately 64%. Rates can be higher in certain age groups, countries, or populations, which may explain higher figures found elsewhere.
Does 67% of the population have herpes?
An older WHO estimate based on 2016 data placed HSV-1 prevalence among people aged 0–49 at approximately 67%. The updated 2020 estimate is approximately 64%, or 3.8 billion people under age 50.
How common is HSV-2?
Approximately 13% of people aged 15–49 worldwide were estimated to have HSV-2 in 2020, equivalent to around 520 million people.
How common is herpes in the United States?
CDC data from 2015–2016 found HSV-1 in 47.8% and HSV-2 in 11.9% of people aged 14–49. These figures should be interpreted according to the study period rather than treated as newly measured 2026 rates.
Can someone spread herpes without symptoms?
Yes. HSV can be transmitted even when visible sores are absent, which is one reason many infections go unrecognized.
Conclusion
So, how many percentage of people have herpes? The clearest answer is that approximately 64% of people under age 50 worldwide have HSV-1, around 13% of people aged 15–49 have HSV-2, and more than 20% of people aged 15–49 are estimated to have genital herpes from HSV-1, HSV-2, or both.
Herpes is therefore one of the world’s most common viral infections, and many people who carry HSV never know they have it. Statistics can provide useful context, but they cannot determine an individual’s infection status; anyone concerned about symptoms, exposure, testing, pregnancy, or treatment should speak with a qualified healthcare professional.


Volglaswanden: Voordelen, Kosten en Tips

triple whale discount code: Save on Your Plan

BBT Slow to Rise After Ovulation: Causes, Charts & What to Do
-

 Fashion9 years ago
These ’90s fashion trends are making a comeback in 2017
-
Entertainment9 years ago
The final 6 ‘Game of Thrones’ episodes might feel like a full season
-
Fashion9 years ago
According to Dior Couture, this taboo fashion accessory is back
-
Business9 years ago
Uber and Lyft are finally available in all of New York State
-
Entertainment9 years ago
The old and New Edition cast comes together to perform
-
Sports9 years ago
Steph Curry finally got the contract he deserves from the Warriors
-
Sports9 years ago
Phillies’ Aaron Altherr makes mind-boggling barehanded play
-
Entertainment9 years ago
Disney’s live-action Aladdin finally finds its stars